1. Introduction to Infective Conjunctivitis
Infective conjunctivitis, widely recognized in the community as “pink eye,” is a common inflammatory condition of the outermost layer of the eye and the inner surface of the eyelids. The immediate clinical outcome is localized vasodilation, resulting in a distinctly red or pink appearance of the eye, accompanied by varied forms of discharge and ocular discomfort. Prompt clinical assessment is necessary to differentiate the causative agent and prevent transmission.
The conjunctiva is continuously exposed to the external environment, making it vulnerable to diverse microbial pathogens. However, it possesses robust localized immune defenses. Infections occur when an invading virus or bacterium overwhelms these defenses, triggering a localized inflammatory cascade. The specific nature of the pathogen dictates the clinical presentation, the severity of the symptoms, and the subsequent medical management.
Accurate differentiation between viral and bacterial etiologies is a primary clinical objective. This distinction is vital to limit the unnecessary prescription of topical antibiotics, reduce the risk of antimicrobial resistance, and implement appropriate infection control measures, particularly in school or daycare environments.
2. Anatomy and Defense of the Conjunctiva
The conjunctiva is a thin, transparent, highly vascularized mucous membrane. It lines the posterior aspect of the eyelids (palpebral conjunctiva) and reflects back to cover the anterior sclera (bulbar conjunctiva), terminating at the edge of the cornea. Its primary function is to secrete the mucin and aqueous components of the tear film, maintaining ocular lubrication and providing a protective barrier.
The tear film itself is a formidable defensive mechanism. It physically flushes foreign debris and pathogens away from the ocular surface. Furthermore, the tears contain potent antimicrobial enzymes, specifically lysozyme and lactoferrin, as well as secretory immunoglobulin A, which actively neutralize invading microorganisms.
When these defenses are breached, typically through direct inoculation via contaminated hands, the pathogen colonizes the mucosal epithelial cells. The resulting inflammatory response causes the dense network of tiny conjunctival blood vessels to engorge and become highly visible against the white sclera, producing the characteristic hyperemic appearance.
3. Pathophysiology of Viral Infections
Viruses are the most common cause of infective conjunctivitis, accounting for the vast majority of cases in adults. Adenovirus is the predominant viral pathogen. These viruses possess specialized surface proteins that allow them to bind efficiently to the receptors on the conjunctival epithelial cells.
Once attached, the virus enters the cell and utilizes the host’s machinery for viral replication, ultimately leading to cellular death and the release of new virions. This process triggers a localized immune response dominated by lymphocytes. The viral-induced inflammation primarily causes an increase in tear production and localized edema, resulting in a watery discharge.
Adenoviral infections are notoriously contagious and frequently present alongside or immediately following an upper respiratory tract infection. The virus can survive for extended periods on environmental surfaces, facilitating rapid spread through shared towels, medical instruments, or direct hand-to-eye contact.
4. Bacterial Colonization Mechanisms
Bacterial conjunctivitis is less common than viral etiologies in adults but occurs frequently in the pediatric population. Pathogens such as Staphylococcus aureus, Streptococcus pneumoniae, and Haemophilus influenzae are the usual culprits. These bacteria often reside benignly in the upper respiratory tract but can become opportunistic pathogens when introduced to the ocular surface.
Bacterial invasion triggers an immune response heavily dominated by polymorphonuclear leukocytes (neutrophils). These immune cells rapidly migrate to the conjunctiva to engulf and destroy the bacteria. The accumulation of dead neutrophils, bacteria, and epithelial debris forms a thick, opaque, mucopurulent discharge.
This robust inflammatory response often leads to the formation of papillae—small, elevated vascular tufts on the palpebral conjunctiva, giving the inner eyelid a velvety appearance. The continuous production of purulent exudate frequently causes the eyelids to adhere tightly together, particularly upon waking in the morning.
5. Transmission Pathways and Contagion
The primary mechanism of transmission for both viral and bacterial conjunctivitis is direct contact. The pathogen is typically transferred from the hands of an infected individual directly to their own eye, or to environmental surfaces, and subsequently to the eyes of a susceptible host.
The highly infectious nature of the ocular secretions makes diligent hygiene paramount. Sharing personal items, such as cosmetics, pillows, or towels, acts as a direct conduit for the transfer of a large infectious dose. Furthermore, improperly cleaned contact lenses or shared contact lens solutions provide an optimal environment for microbial proliferation.
In healthcare settings, rigorous decontamination of ophthalmic equipment, such as tonometers and slit lamps, is strictly enforced to prevent iatrogenic outbreaks of epidemic keratoconjunctivitis, a severe adenoviral infection that can cause prolonged morbidity.
6. Clinical Presentation of Viral Conjunctivitis
Patients with viral conjunctivitis typically present with a distinctly pink or red eye, initially affecting one eye before rapidly spreading to the other within a few days. The discharge is characteristically thin, clear, and watery, mimicking the appearance of excess tearing.
The patient frequently complains of a foreign body sensation—a gritty feeling as if sand is trapped in the eye. Severe pain or profound light sensitivity (photophobia) are generally absent in simple viral conjunctivitis; their presence suggests a more serious ocular complication.
A key diagnostic finding in viral etiologies is the presence of a palpable, tender preauricular lymph node located just in front of the ear. This localized lymphatic swelling, combined with a concurrent runny nose or sore throat, strongly supports a viral diagnosis. This presentation shares clinical overlap with systemic viral conditions discussed in our guide on viral fever management.
7. Clinical Presentation of Bacterial Conjunctivitis
Bacterial conjunctivitis typically presents with a sudden onset of symptoms, often involving both eyes simultaneously or in rapid succession. The conjunctival redness is usually pronounced. The hallmark clinical feature is the continuous production of a thick, opaque, yellowish-green mucopurulent discharge.
Unlike the watery discharge of a viral infection, this purulent exudate rapidly reaccumulates after being wiped away. Patients classically report that their eyelids are “glued shut” upon waking in the morning, requiring warm water to soften the crusted discharge before the eyes can be opened.
While the eye may feel mildly irritated or burning, significant pain and visual changes are uncommon. The preauricular lymph nodes are generally not enlarged in routine bacterial conjunctivitis, serving as a helpful differentiating factor during clinical examination.
8. Chlamydial and Gonococcal Infections
While most bacterial conjunctivitis is caused by common respiratory pathogens, Neisseria gonorrhoeae and Chlamydia trachomatis represent severe, distinct clinical entities requiring urgent, specialized management. These pathogens are typically transmitted to the eye via autoinoculation from an infected genital site.
Gonococcal conjunctivitis is a hyperacute, sight-threatening emergency. It presents with massive, profuse purulent discharge that literally streams from the eye, accompanied by severe conjunctival swelling (chemosis). The gonococcus possesses specific enzymes that can rapidly digest intact corneal tissue, leading to corneal perforation and permanent blindness within days if untreated.
Chlamydial conjunctivitis (inclusion conjunctivitis) follows a more indolent, chronic course, often persisting for weeks despite standard topical antibiotic therapy. It characteristically presents with large lymphoid follicles on the palpebral conjunctiva. Both conditions mandate immediate systemic antibiotic therapy rather than just topical drops.
9. Ophthalmia Neonatorum
Infective conjunctivitis in a newborn, termed ophthalmia neonatorum, is a distinct clinical category that occurs within the first four weeks of life. The infection is primarily acquired during passage through an infected birth canal. The causative agents range from chemical irritants to severe bacterial pathogens like Chlamydia and Gonorrhea.
Due to the devastating potential of gonococcal infection in neonates, prophylactic administration of topical erythromycin or tetracycline ointment into the eyes of all newborns immediately after birth is a standard public health protocol worldwide.
Any conjunctivitis in a neonate requires an immediate, exhaustive clinical evaluation, including cultures of the ocular discharge, to definitively rule out Chlamydia or Gonorrhea, as these infections require prompt systemic intravenous antibiotics to prevent severe systemic dissemination and permanent visual impairment.
10. Diagnostic Evaluation and Slit-Lamp Exam
In routine clinical practice, the diagnosis of infective conjunctivitis is primarily made based on a detailed patient history and macroscopic visual inspection. The clinician assesses the nature of the discharge, the pattern of redness, and the presence of associated systemic symptoms.
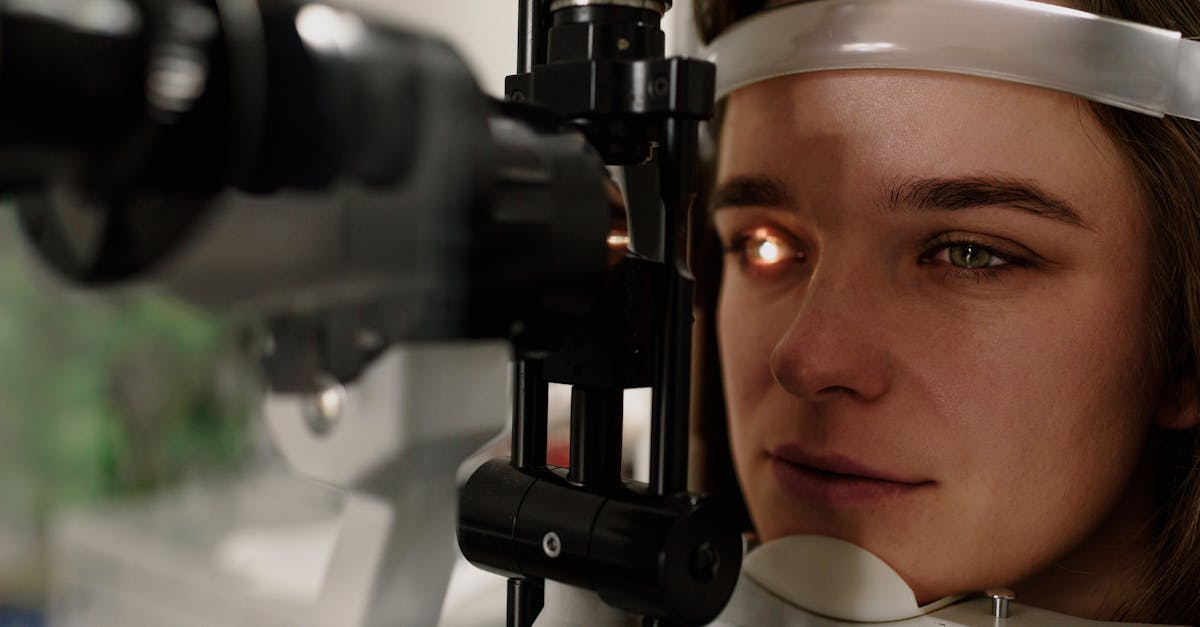
When a patient presents to an ophthalmologist, a slit-lamp biomicroscopic examination is performed. This highly magnified evaluation allows the clinician to inspect the palpebral conjunctiva for specific inflammatory patterns, such as follicles (suggestive of viral or chlamydial infection) or papillae (suggestive of bacterial or allergic reactions).
The clinician also carefully evaluates the cornea using a specialized fluorescent dye to rule out viral keratitis or bacterial corneal ulcers, which require vastly different and more aggressive treatment protocols than simple conjunctivitis.
11. Structured Diagnostic Differentiation
The following table highlights the distinct clinical features used by clinicians to differentiate between the primary etiologies of conjunctival inflammation.
| Diagnostic Feature | Viral Conjunctivitis | Bacterial Conjunctivitis | Allergic Conjunctivitis |
|---|---|---|---|
| Nature of Discharge | Watery, clear | Thick, purulent, yellow/green | Stringy, white mucus |
| Primary Sensation | Gritty, foreign body sensation | Burning, mild irritation | Intense, severe itching |
| Lymph Node Swelling | Preauricular node often enlarged | Typically normal | Normal |
| Systemic Association | Recent cold or respiratory infection | Sometimes sinus or ear infection | Seasonal allergies, asthma |
12. Management of Bacterial Conjunctivitis
Mild, uncomplicated bacterial conjunctivitis is often a self-limiting disease, clearing in one to two weeks without intervention. However, the administration of topical broad-spectrum antibiotics significantly accelerates clinical resolution and reduces the duration of transmissibility.
Ophthalmic solutions or ointments containing medications such as polymyxin B/trimethoprim, erythromycin, or a fluoroquinolone are typically prescribed for five to seven days. Ointments are frequently preferred for children as they maintain contact with the ocular surface longer and are easier to apply than drops.
Patients who wear contact lenses require specific attention. They must immediately discontinue lens wear and discard their current lenses and case. Their antibiotic regimen must include specific coverage for Pseudomonas aeruginosa, a virulent bacterium associated with contact lens wear that rapidly causes severe corneal damage.
13. Supportive Care for Viral Conjunctivitis
There are no effective topical antiviral medications for standard adenoviral conjunctivitis. The clinical management is entirely supportive, focusing on symptom palliation while the host’s immune system clears the virus, a process that can take up to three weeks.
Artificial tear drops, preferably preservative-free, are recommended to dilute inflammatory mediators and soothe the gritty sensation. Cold compresses applied to the closed eyelids several times a day cause localized vasoconstriction, substantially reducing swelling and discomfort.
Topical corticosteroids are generally avoided in routine cases. While they rapidly suppress inflammation, they impair the local immune response, potentially prolonging viral shedding. They are strictly reserved for severe cases involving visual impairment, administered only under the direct supervision of an ophthalmologist.
14. Complications and Corneal Involvement
While typically a superficial infection, severe cases can involve the cornea, a condition termed keratoconjunctivitis. Adenoviral infections can cause subepithelial infiltrates—small, cloudy immune cell collections beneath the corneal surface. These infiltrates can cause significant glare, halos around lights, and decreased visual acuity lasting for months.
A critical complication is the formation of a pseudomembrane, a thick, adherent layer of inflammatory exudate and necrotic cells that forms on the inner eyelid. This membrane causes severe mechanical irritation to the cornea and must be physically peeled away by a physician to allow the underlying tissue to heal and topical medications to penetrate.
Any patient experiencing a sudden decrease in vision, severe deep ocular pain, or extreme light sensitivity must be evaluated emergently, as these signs suggest the infection has compromised the cornea or penetrated deeper into the globe of the eye.
15. Frequently Asked Questions
1. How long is pink eye contagious?
Viral conjunctivitis is highly contagious for as long as the eyes remain red and weeping, often up to two weeks. Bacterial conjunctivitis generally remains contagious until the patient has been using antibiotic drops for at least 24 hours.
2. Why won’t my doctor prescribe antibiotics for my watery, red eyes?
If the discharge is clear and watery and accompanied by cold symptoms, it is almost certainly a viral infection. Antibiotics cannot kill viruses; using them unnecessarily contributes to antibiotic resistance and can cause allergic reactions.
3. Can I continue to wear my contact lenses if I have a mild eye infection?
Absolutely not. Wearing contact lenses traps the bacteria or virus against the eye, severely compounding the infection and vastly increasing the risk of a permanent, sight-threatening ulcer developing on your cornea.
4. What is the best way to clean my eyes when they are crusted shut?
Wash your hands thoroughly, then soak a clean washcloth or cotton pad in warm water. Hold it gently against your closed eye for a few minutes to soften the crust, then gently wipe outward from the nose. Discard the pad or wash the cloth immediately.
5. Do I need to throw away my eye makeup?
Yes. Any mascara, eyeliner, or eyeshadow utilized immediately before or during the infection is highly contaminated. Reusing these products will simply re-infect your eyes once the current episode clears.
16. Bibliography
Disclaimer: The content is for informational purposes only and does not replace medical advice. Always consult your doctor for personalized treatment.