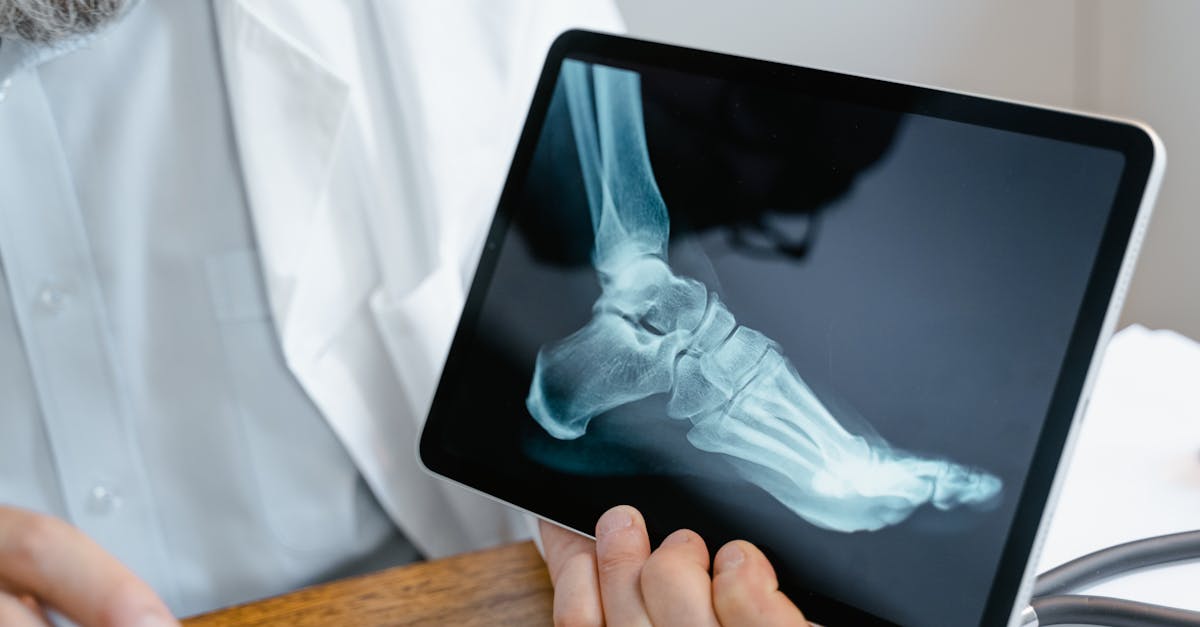
1. Introduction to Ankle Joint Pain
Pain in the ankle joint is a highly frequent clinical presentation that originates from acute mechanical trauma, repetitive soft tissue overuse, or progressive degenerative wear. Because the ankle acts as the primary weight-bearing hinge of the lower extremity, it is subjected to immense physical forces with every step, making its intricate network of ligaments and cartilage highly vulnerable to injury and breakdown. Prompt diagnosis is vital to prevent minor acute injuries from evolving into states of chronic instability and debilitating joint pain.
Clinical evaluation focuses heavily on identifying the specific mechanism of injury and precisely mapping the anatomical location of the pain. Differentiating between a straightforward ligamentous sprain, a subtle occult fracture, or an active inflammatory arthropathy dictates the entirely of the subsequent treatment protocol.
A thorough understanding of the ankle’s unique biomechanical demands ensures that the clinical management strategy not only rapidly controls acute inflammation but also comprehensively restores the necessary neuromuscular control required for safe ambulation and return to sporting activities.
2. Structural Anatomy of the Ankle Complex
The ankle joint is a highly complex, multi-articular hinge structure comprising two primary articulations: the tibiotalar (true ankle) joint and the subtalar joint. The tibiotalar joint is formed by the distal ends of the tibia and fibula, which create a deep mortise, or socket, that securely grips the dome of the talus bone. This specific articulation primarily permits the up-and-down movements of dorsiflexion and plantarflexion.
Immediately beneath the talus lies the subtalar joint, which connects the talus to the calcaneus (heel bone). This secondary joint facilitates the crucial side-to-side rotational movements known as inversion and eversion, allowing the foot to adapt to uneven terrain during walking.
The structural stability of the ankle complex relies entirely on its dense ligamentous support. The lateral aspect is secured by the anterior talofibular, calcaneofibular, and posterior talofibular ligaments. The medial aspect is stabilized by the massive, fan-shaped deltoid ligament. A specialized syndesmotic ligament complex tightly binds the distal tibia and fibula together, preventing them from splaying apart under the immense load of bearing body weight.
3. Acute Lateral Ankle Sprains
The acute lateral ankle sprain is unequivocally the most common musculoskeletal injury encountered in clinical practice. It occurs when the foot is forcefully inverted (rolled inward) and plantarflexed, a movement that rapidly stretches the lateral ligament complex beyond its physiological limit. The anterior talofibular ligament is the weakest component and is nearly always the first structure to tear.
Patients present with immediate, sharp pain on the outside of the ankle, often recalling a distinct “pop” or tearing sensation at the moment of injury. The area rapidly develops profound soft tissue swelling and dependent ecchymosis (bruising) that tracks down toward the toes. Weight-bearing becomes significantly painful and mechanically unstable.
Sprains are clinically graded from I to III based on the severity of the ligamentous tearing. While Grade I sprains involve mild microscopic stretching, Grade III sprains represent a complete macroscopic rupture of the ligaments, resulting in gross joint laxity that requires extensive rehabilitation to restore functional stability.
4. High Ankle Sprains (Syndesmotic Injuries)
A high ankle sprain represents a severe structural injury to the syndesmotic ligaments that securely bind the tibia and fibula together above the true ankle joint. This injury mechanism typically involves a forceful external rotation of the foot combined with dorsiflexion, commonly occurring in contact sports or when a ski suddenly catches an edge.
The powerful rotational force violently pries the tibia and fibula apart, tearing the intervening syndesmotic tissue. Patients describe severe pain located slightly higher up the leg, above the ankle joint line. Unlike a lateral sprain, the external swelling is often deceptively minimal, leading patients to underestimate the severity of the structural damage.
Clinical diagnosis involves specific provocative testing, such as the squeeze test or external rotation stress test, which actively separate the bones to reproduce the deep pain. High ankle sprains mandate a significantly prolonged recovery period compared to standard sprains and often require strict non-weight-bearing immobilization or surgical fixation to prevent long-term joint destruction.
5. Chronic Ankle Instability
Chronic ankle instability is a debilitating clinical condition that frequently develops following recurrent, inadequately rehabilitated acute lateral ankle sprains. When the torn ligaments heal in a stretched, lax position, they fail to provide the necessary static mechanical restraint.
Furthermore, the initial trauma frequently damages the microscopic proprioceptive nerve endings within the joint capsule. This neurological deficit severely impairs the body’s ability to sense the exact position of the joint in space, delaying the protective muscular reflexes necessary to prevent the ankle from rolling during dynamic activity.
Patients with chronic instability report a constant, deep aching pain and a persistent sensation that the ankle is “giving way” or completely untrustworthy on uneven ground. Comprehensive physical therapy targeting proprioceptive retraining and dynamic muscular stabilization is critical. If non-operative measures fail, surgical ligament reconstruction is required to physically tighten the lateral complex.
6. Achilles Tendinopathy and Posterior Pain
Pain located at the back of the ankle is most frequently attributed to pathology of the Achilles tendon, the thickest and strongest tendon in the human body. Achilles tendinopathy is an overuse injury characterized by chronic, painful cellular degeneration within the tendon tissue, typically occurring two to six centimeters above its insertion point on the calcaneus, an area with a notoriously poor blood supply.
This condition is highly prevalent in runners and athletes involved in explosive jumping activities. Patients experience a severe, burning ache and noticeable stiffness in the posterior ankle, particularly pronounced upon taking the first steps in the morning. A localized, painful nodule or generalized thickening of the tendon is frequently palpable during clinical examination.
Management requires strict activity modification to halt repetitive microtrauma. A structured physical therapy program emphasizing eccentric calf strengthening exercises is the gold standard for stimulating collagen remodeling and restoring the structural integrity of the diseased tendon.
7. Osteoarthritis of the Tibiotalar Joint
While osteoarthritis of the knee and hip is largely driven by age and primary mechanical wear, osteoarthritis of the ankle is overwhelmingly post-traumatic in nature. It typically develops years or even decades after a severe ankle fracture, significant joint dislocation, or long-standing chronic joint instability.
The prior trauma irreparably damages the articular cartilage or permanently alters the joint biomechanics, leading to accelerated friction and subsequent joint space narrowing. Patients report a deep, progressive ache within the joint that intensifies with weight-bearing activities and is accompanied by significant, progressive stiffness and a visible loss of dorsiflexion.
Extensive osteophyte (bone spur) formation around the anterior joint line frequently causes a sharp, pinching pain when the patient attempts to bring the foot upward toward the shin. Treatment focuses on load modification, the use of specialized rocker-bottom footwear, and in end-stage disease, surgical joint fusion or total ankle replacement.
8. Tarsal Tunnel Syndrome
Tarsal tunnel syndrome is a highly specific entrapment neuropathy involving the compression of the posterior tibial nerve as it travels behind the medial malleolus (the inner ankle bone) and beneath a tight fibrous band called the flexor retinaculum.
Nerve compression can be triggered by rapid localized swelling from a sprain, the presence of a space-occupying lesion like a benign ganglion cyst, or severe biomechanical flatfoot deformity that places continuous traction on the nerve. The resulting neuropathic pain is characteristically described as a burning, electrical, or shooting sensation.
The pain frequently radiates directly from the inner ankle down into the sole of the foot and the toes. Patients may also experience localized numbness or a severe tingling sensation that is characteristically worse at night. Diagnosis is confirmed through electromyography, and treatment ranges from utilizing custom orthotics to correct flatfoot deformity to surgical decompression of the tarsal tunnel.
9. Fractures of the Malleoli
Fractures of the bony prominences of the ankle—the lateral malleolus (fibula), medial malleolus (tibia), and posterior malleolus—result from high-energy rotational trauma or direct physical impact. These are severe injuries that immediately compromise the structural integrity of the entire ankle mortise.
A fractured ankle presents with instant, excruciating pain, profound and rapid swelling, extensive ecchymosis, and a complete, absolute inability to bear any body weight. If the fracture is accompanied by a joint dislocation, a severe, highly visible physical deformity of the limb will be present.
Immediate radiographic evaluation is strictly mandatory. The clinical management of ankle fractures depends entirely on the stability of the joint. Stable, non-displaced fractures may be managed conservatively in a cast, but any displacement that widens the mortise requires urgent open reduction and internal fixation utilizing surgical plates and screws to restore perfect anatomical alignment.
10. Osteochondral Lesions of the Talus
Osteochondral lesions are localized injuries affecting both the smooth articular cartilage and the underlying subchondral bone of the talus dome. These defects are overwhelmingly caused by the severe compressive and shearing forces sustained during a severe ankle sprain or acute fracture.
The damaged fragment of cartilage and bone may remain partially attached or break completely free, floating loosely within the joint space. Patients describe a deep, poorly localized, aching pain deep within the ankle joint. The clinical hallmark of a loose osteochondral fragment is the presence of distinct mechanical symptoms, such as the joint suddenly catching, locking, or clicking painfully during normal walking.
Standard X-rays frequently miss these subtle defects; thus, magnetic resonance imaging is the gold standard for definitive diagnosis. Symptomatic lesions that do not heal with rest require arthroscopic surgical debridement or sophisticated cartilage grafting procedures.
11. Gout and Inflammatory Arthropathies
Systemic inflammatory conditions frequently target the highly vascularized synovial lining of the ankle joint. Gout is a severely painful, acute crystal arthropathy caused by the intra-articular deposition of uric acid crystals. An acute gout flare in the ankle presents with explosive, overnight onset of agonizing pain, immense swelling, and intense redness, making the joint exquisitely tender to even the lightest touch.
Rheumatoid arthritis is an aggressive autoimmune disorder that causes chronic, symmetrical inflammation of the ankle and foot joints. The hyperactive immune system drives profound synovitis, leading to significant morning stiffness and the gradual, destructive erosion of the articular cartilage and subchondral bone.
Accurate diagnosis necessitates comprehensive serological blood testing and synovial fluid analysis. Immediate initiation of targeted disease-modifying therapies is paramount to suppress the systemic inflammation and prevent irreversible structural joint deformity.
12. Posterior Tibial Tendon Dysfunction
Posterior tibial tendon dysfunction is the leading cause of acquired flatfoot deformity in adults. This powerful tendon travels behind the medial malleolus and is absolutely critical for maintaining the structural height of the medial longitudinal arch of the foot during walking.
Chronic repetitive overload leads to the progressive degeneration, elongation, and eventual tearing of the tendon. Patients initially present with a deep, aching pain and visible swelling directly along the inner aspect of the ankle. As the tendon progressively fails, the medial arch collapses completely, and the heel bone tilts outward into a severe valgus position.
In the late stages of the disease, the pain severely shifts to the lateral (outer) aspect of the ankle as the collapsing bones painfully impinge upon the fibula. Early intervention utilizing rigid custom orthotics and physical therapy is essential to support the arch; advanced deformity requires complex surgical bony reconstruction.
13. Clinical Presentation and Symptoms
A meticulous clinical analysis of the specific location and mechanical triggers of the pain directs the clinician toward an accurate anatomical diagnosis.
| Pain Location and Characteristics | Common Associated Diagnosis |
|---|---|
| Sudden outer ankle pain and swelling after rolling the foot | Acute Lateral Ankle Sprain |
| Pain above the joint line, worsening when foot is twisted outward | Syndesmotic (High) Ankle Sprain |
| Burning pain and numbness along inner ankle and sole of foot | Tarsal Tunnel Syndrome |
| Deep, progressive ache with severe morning stiffness | Ankle Osteoarthritis (often post-traumatic) |
Any ankle pain resulting from acute trauma that immediately prevents the patient from taking four consecutive steps mandates urgent radiographic assessment according to the Ottawa Ankle Rules to rule out a fracture.
14. Diagnostic Imaging: X-rays to MRI
The clinical examination of the ankle involves precise palpation of bony landmarks, assessing the integrity of specific ligaments through manual stress testing, and observing the patient’s biomechanical gait pattern. Standard weight-bearing plain radiographs (X-rays) are the universally accepted first line of imaging, rapidly identifying fractures, large osteochondral defects, and the joint space narrowing indicative of arthritis.
When occult fractures or significant soft tissue pathology are suspected, magnetic resonance imaging provides unparalleled anatomical resolution. MRI is highly sensitive for identifying full-thickness ligamentous tears, subtle bone marrow edema, severe tendon degeneration, and the precise size of osteochondral lesions of the talus.
Diagnostic ultrasound is increasingly utilized for the dynamic, real-time assessment of tendon gliding and for accurately guiding therapeutic corticosteroid injections into inflamed tendon sheaths or the true ankle joint space.
15. Conservative Treatment and Immobilization
The initial management of acute ankle injuries adheres to the strict protocol of protection, rest, ice, compression, and elevation. Immediate joint protection is achieved through the use of functional braces, rigid walking boots, or crutches to strictly limit mechanical weight-bearing and halt the localized inflammatory cascade.
Pharmacological intervention utilizes oral nonsteroidal anti-inflammatory drugs to mitigate acute pain and reduce soft tissue edema. For chronic, severe intra-articular pain due to osteoarthritis, targeted intra-articular corticosteroid injections provide potent, localized suppression of the inflammatory response, significantly improving joint mobility.
Biomechanical correction through the use of specialized, custom-molded orthotics is a fundamental component of managing posterior tibial tendon dysfunction and chronic plantar fasciitis, directly reducing the non-physiological stress placed upon the healing soft tissues.
16. Physical Therapy and Surgical Options
Physical therapy is the absolute cornerstone of comprehensive ankle rehabilitation. Following an acute sprain, physical therapy focuses on early mobilization to prevent severe capsular stiffness. The core of the program involves aggressive proprioceptive retraining utilizing balance boards and dynamic functional strengthening of the peroneal muscles to restore full dynamic joint stability.
Surgical intervention is indicated when extensive conservative measures fail or in the presence of acute, unstable structural damage. Open reduction and internal fixation are required for displaced fractures. Chronic, severe lateral instability necessitates surgical ligamentous reconstruction, frequently utilizing the Broström-Gould procedure to physically tighten the torn lateral complex.
In cases of end-stage, debilitating osteoarthritis, the clinician may recommend a surgical ankle arthrodesis (fusion) to completely eliminate the painful joint movement, or a total ankle arthroplasty (replacement) to preserve functional joint motion in appropriately selected patients.
17. Frequently Asked Questions (FAQ)
1. Should I walk on a sprained ankle?
You should not walk on a newly sprained ankle if it causes significant pain or if you walk with a severe limp. Doing so can increase tissue damage and swelling. You must use crutches or a walking boot until a clinician confirms it is safe to bear weight.
2. Why does my ankle pop and click when I walk?
Painless popping is often caused by a tight tendon snapping over a bony ridge, or gas bubbles releasing in the joint. However, if the clicking is accompanied by a sharp, deep pain or a feeling of the joint locking, it strongly indicates a loose cartilage fragment requiring medical evaluation.
3. Will a high ankle sprain heal on its own?
High ankle sprains heal significantly slower than standard sprains. While mild cases heal with prolonged rest and specialized bracing in a walking boot, severe high ankle sprains that separate the bones require surgical screw fixation to heal properly and prevent long-term arthritis.
4. How do I know if my ankle is broken or just severely sprained?
It is clinically impossible to definitively differentiate a severe sprain from a fracture without an X-ray. Both cause immense pain, rapid swelling, and bruising. If you cannot bear weight to take four consecutive steps immediately after the injury, you must seek an urgent X-ray.
5. What is the best shoe for ankle arthritis?
A shoe with a rigid, rocker-bottom sole is highly effective for ankle arthritis. The curved sole physically rolls the foot forward during the walking cycle, significantly reducing the amount of painful bending motion required from the arthritic ankle joint itself.
Bibliography
Disclaimer: The content is for informational purposes only and does not replace medical advice. Always consult your doctor for personalized treatment.