1. Introduction
A severely swollen sprained ankle typically reaches its maximum volume within forty-eight hours and takes two to four weeks for the visible swelling to significantly subside. The duration of this intense localized swelling is directly proportional to the severity of the structural damage sustained by the lateral ligaments. While the acute puffiness and bruising fade within the first month, a mild, residual swelling often lingers around the ankle bone for several months, particularly after prolonged standing or strenuous physical activity. Implementing aggressive conservative management immediately following the injury is vital to accelerate the clearance of this inflammatory fluid and restore joint mechanics.
2. Anatomy of the Ankle Ligaments
The ankle is a highly complex hinge joint that must support the entire weight of the human body while adapting to uneven terrain. Stability is provided by a precise configuration of bones—the tibia, fibula, and talus—bound tightly together by strong, fibrous bands of connective tissue called ligaments.
The lateral aspect, or outside of the ankle, is the most vulnerable to injury. It is supported by three primary ligaments: the anterior talofibular ligament, the calcaneofibular ligament, and the posterior talofibular ligament. These structures act as rigid check-reins, allowing the foot to point up and down but actively preventing it from tilting too far inward.
3. The Mechanism of an Inversion Injury
The vast majority of severe ankle sprains occur via an inversion mechanism. This happens when a person steps awkwardly on an uneven surface, rolls off a curb, or lands poorly from a jump. The foot is violently forced inward, while the body’s weight continues to drive downward.
This sudden, massive mechanical force places extreme tensile stress on the lateral ligaments. If the force exceeds the structural elasticity of the tissue, the collagen fibers begin to tear. The anterior talofibular ligament is almost always the first to fail, followed by the calcaneofibular ligament in more severe trauma. This violent tearing of tissue is the precise catalyst for the ensuing massive swelling.
4. Pathophysiology of Tissue Swelling
The immediate swelling that balloons around the lateral ankle bone, the lateral malleolus, is the result of internal bleeding and an acute inflammatory cascade. When the ligaments tear, the microscopic blood vessels embedded within and surrounding the connective tissue also rupture. Blood rushes into the interstitial spaces, forming a localized hematoma.
Simultaneously, the damaged cells release potent chemical messengers, including histamine and bradykinin. These chemicals cause the surrounding intact capillaries to dilate massively and become highly permeable. This allows blood plasma and white blood cells to flood out of the vascular system and into the injured joint capsule, creating the dense, heavy swelling characteristic of a fresh sprain.
5. Grading Ankle Sprains
The duration of the swelling and the overall recovery timeline depend heavily on the clinical grade of the sprain.
| Clinical Grade | Ligament Status | Swelling Profile and Recovery Time |
|---|---|---|
| Grade I (Mild) | Microscopic stretching, no gross tearing. | Mild, localized puffiness; resolves in 1 to 2 weeks. |
| Grade II (Moderate) | Partial tearing of the collagen fibers. | Moderate to severe swelling and bruising; takes 3 to 6 weeks. |
| Grade III (Severe) | Complete rupture of one or more ligaments. | Massive, diffuse swelling; takes several months for full resolution. |
A precise diagnosis dictates the aggressiveness of the required rehabilitation protocol.
6. The Role of the Lymphatic System
Clearing the massive volume of fluid trapped in the ankle relies entirely on the lymphatic system. Unlike the circulatory system, which uses the heart as a pump, the lymphatic system has no central pump. It relies exclusively on the mechanical contraction of the surrounding calf muscles to push the fluid upward, against gravity, toward the lymph nodes behind the knee and in the groin.
When an ankle is severely sprained, the intense joint pain causes the patient to limp or avoid moving the joint entirely. Without this vital muscle pumping action, the inflammatory fluid stagnates around the joint. This stagnation is why a sprained ankle can remain grossly swollen for weeks if the patient does not actively participate in rehabilitation.
7. Acute Management Protocols
The immediate management of a severe sprain dictates the trajectory of the healing process. The acronym standard for acute care is moving from RICE to the more modern PEACE and LOVE protocol. In the first few days, Protection, Elevation, Avoid anti-inflammatories, Compression, and Education are prioritized.
Elevation is arguably the most critical physical intervention for swelling. The ankle must be elevated strictly above the level of the heart to utilize gravity effectively. Sitting in a chair with the foot on a low stool is entirely insufficient; the fluid will not drain. Compression via a firm, elastic bandage provides external pressure that forces the interstitial fluid back into the lymphatic vessels and prevents new fluid from accumulating in the tissue spaces.
8. The Transition to Mobility
After the initial seventy-two hours of acute inflammation have passed, the focus shifts to restoring mobility. Prolonged immobilization in a rigid boot or cast, once standard practice, is now discouraged for most sprains as it leads to profound joint stiffness, muscle atrophy, and chronic, lingering swelling.
Early, pain-free range-of-motion exercises, such as tracing the alphabet in the air with the big toe, are essential. These micro-movements activate the calf muscles, restarting the lymphatic pump and physically flushing the thick, stagnant fluid out of the joint capsule. The mechanical load also signals the fibroblasts to begin laying down new collagen fibers in proper alignment.
9. Proprioception and Neuromuscular Control
A severely swollen ankle fundamentally alters the body’s neurological connection to the foot. The ligaments contain specialized nerve endings called mechanoreceptors, which constantly inform the brain about the ankle’s position in space. When the ligament is torn, these sensors are destroyed.
This loss of proprioception means the brain no longer knows exactly where the foot is, leaving the patient highly susceptible to rolling the ankle again. Rehabilitation must include balance training, such as standing on one leg on an unstable surface, to force the nervous system to grow new sensory pathways. Failing to complete this phase is the primary cause of chronic ankle instability.
10. Potential Complications of Unresolved Swelling
If massive swelling is left unchecked and the fluid remains stagnant for months, it can cause long-term structural issues. The proteins within the inflammatory fluid can begin to organize and form fibrotic scar tissue inside the joint capsule. This internal scarring physically blocks the normal gliding motion of the bones, leading to a permanent restriction in range of motion.
Furthermore, chronic swelling stretches the skin and superficial nerves, causing persistent aching and a feeling of heavy fatigue in the lower leg. Active physical therapy, including specialized manual lymphatic drainage massage, may be necessary to break down this fibrotic tissue and resolve the stubborn edema.
11. Supportive Footwear and Bracing
During the return to weight-bearing activities, the newly forming collagen in the repairing ligaments is fragile and vulnerable to re-tearing. Utilizing external support is a standard clinical recommendation. A semi-rigid lace-up ankle brace provides mechanical stability, preventing the foot from slipping into the dangerous inversion angle.
Proper footwear is equally important. Flimsy, unsupportive shoes or high heels should be strictly avoided. Wearing a sturdy athletic shoe with a wide base of support and a firm heel counter helps keep the rearfoot in a neutral alignment, reducing the workload on the recovering lateral ligaments.
12. Managing Residual Swelling
It is a clinical reality that even with excellent rehabilitation, an ankle that sustained a Grade II or Grade III sprain may continue to exhibit mild swelling at the end of a long day for up to six months. This is known as dependent edema and occurs because the microscopic lymphatic vessels take significant time to fully regenerate.
Patients are advised to manage this residual swelling by continuing to wear a mild compression sleeve during prolonged periods of standing or athletic activity. Elevating the leg for twenty minutes in the evening and performing simple calf raises help clear the daily fluid accumulation and maintain optimal joint mechanics.
13. Warning Signs Requiring Imaging
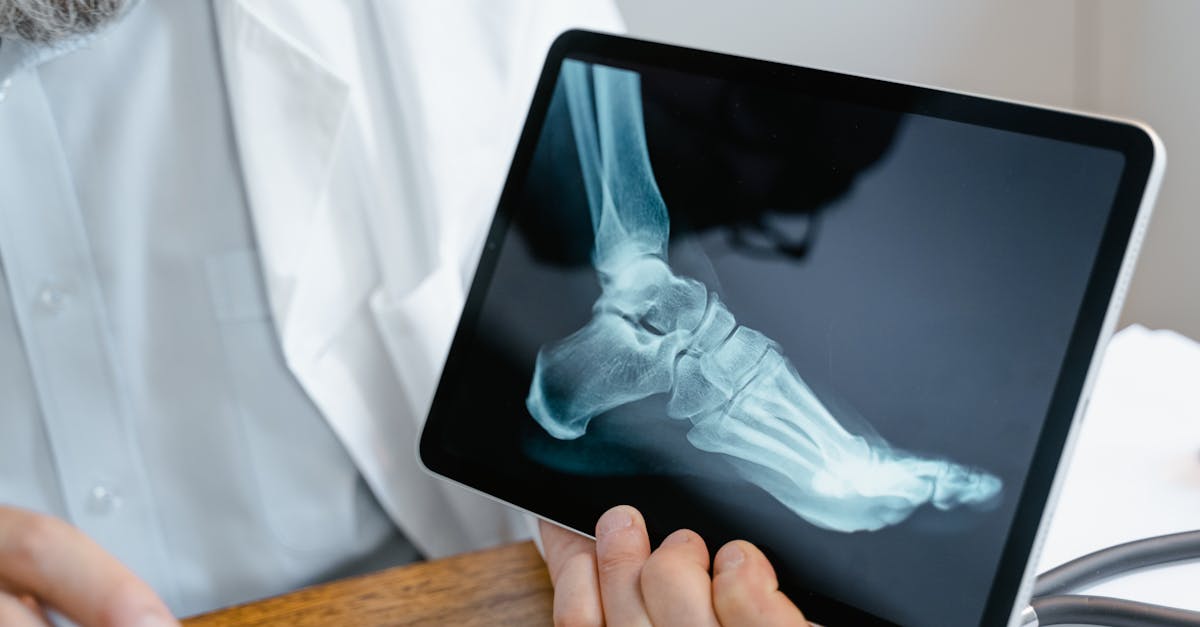
While severe swelling is expected with a bad sprain, certain clinical signs suggest that the injury involves more than just a ligament tear. The Ottawa Ankle Rules are used to determine the necessity of an X-ray. If the patient is entirely unable to bear weight and take four steps immediately after the injury and in the clinical setting, a fracture must be ruled out.
Exquisite, pinpoint bony tenderness directly over the crest of the lateral or medial malleolus, or pain at the base of the fifth metatarsal (the outside of the midfoot), strongly raises the suspicion of an avulsion fracture, where the tearing ligament pulls a small chunk of bone away with it.
14. Long-Term Prognosis and Prevention
The vast majority of severely sprained ankles heal completely and return to full function if the patient adheres to a rigorous rehabilitation program. The newly formed scar tissue remodeling the ligament will eventually mature and provide excellent stability.
Preventing future injuries requires maintaining the strength of the peroneal muscles, which run along the outside of the calf and actively resist ankle inversion. Incorporating lateral stability drills and plyometric exercises into a regular fitness routine ensures that the dynamic muscular defenses of the ankle remain robust enough to protect the joint on uneven terrain, mitigating the risk of recurrent plantar fasciitis or chronic ankle instability.
15. Frequently Asked Questions (FAQ)
1. Is it safe to take ibuprofen immediately after spraining my ankle?
Clinical guidelines now suggest avoiding anti-inflammatory medications for the first forty-eight hours. The initial inflammation is a vital biological process required to clean the wound and start the healing cascade. Suppressing it too early may delay long-term tissue repair.
2. Should I soak my swollen ankle in hot water to reduce the pain?
Absolutely not. Applying heat to a fresh, swollen sprain will cause the blood vessels to dilate massively, pumping more blood into the joint and severely increasing the swelling and throbbing pain. Stick to cold therapy for the first few days.
3. Why is my foot turning purple and yellow down to my toes?
This is normal. Gravity pulls the blood from the torn ligaments downward through the tissues of your foot. As the blood breaks down, it changes color from purple to green to yellow. It looks alarming but is a harmless part of the healing process.
4. Can I sleep with an ice pack on my ankle?
No, leaving ice on for prolonged periods, especially while sleeping, can cause severe frostbite damage to the skin and superficial nerves. Ice should only be applied for fifteen to twenty minutes at a time.
5. When can I start running again?
You should only return to running when you have a full, pain-free range of motion, your ankle strength is equal to your uninjured side, and you can hop on one leg without pain or a feeling of instability.
16. Bibliography
Disclaimer: The content is for informational purposes only and does not replace medical advice. Always consult your doctor for personalized treatment.