
1. Introduction
An ankle injury encompasses structural damage to the bones, ligaments, or tendons that form the ankle joint. This joint is a complex hinge mechanism responsible for bearing the entire weight of the human body while facilitating dynamic movement. When subjected to forces exceeding its physiological capacity, the structural components fail, resulting in sprains, strains, or fractures.
The clinical presentation of an ankle injury typically involves localized pain, swelling, and a variable loss of functional mobility. The severity of the impairment is directly proportional to the extent of anatomical disruption. Distinguishing between a soft tissue injury and an osseous fracture requires a systematic clinical evaluation combined with targeted diagnostic imaging.
Understanding the specific biomechanical forces that cause ankle trauma is essential for accurate diagnosis. Healthcare providers utilize structured assessment protocols to determine the most effective therapeutic interventions, ensuring optimal healing and preventing chronic joint instability.
2. Anatomy of the Ankle Joint
The ankle joint, anatomically known as the talocrural joint, is formed by the articulation of three bones: the tibia, the fibula, and the talus. The distal ends of the tibia and fibula create a mortise, a specialized concave receptacle that securely houses the dome of the talus. This bony architecture provides inherent stability, particularly during weight-bearing activities.
Ligamentous complexes reinforce this bony structure. The lateral collateral ligament complex, consisting of the anterior talofibular ligament, the calcaneofibular ligament, and the posterior talofibular ligament, stabilizes the outer aspect of the joint. The medial aspect is supported by the deltoid ligament, a robust, fan-shaped structure that resists excessive outward angulation.
The syndesmosis is a critical fibrous joint connecting the distal tibia and fibula. It is stabilized by the anterior and posterior inferior tibiofibular ligaments. Disruption of this syndesmotic complex fundamentally destabilizes the mortise, requiring prolonged rehabilitation and often surgical repair.
3. Biomechanics of Ankle Trauma
Injuries occur when the ankle is forced beyond its normal range of motion. The most frequent mechanism of injury involves forced inversion and plantarflexion. This occurs when the foot rolls inward while the toes point downward. This specific movement places immense tensile stress on the lateral ligaments, leading to the classic lateral ankle sprain.
Eversion injuries, where the foot rolls outward, are less common due to the structural strength of the medial deltoid ligament and the anatomical length of the lateral malleolus. When an eversion force is substantial, it often results in an avulsion fracture of the medial malleolus rather than an isolated ligamentous tear.
Rotational forces, particularly when the foot is planted firmly on the ground and the leg twists, can transmit stress through the syndesmosis and up the fibula. These complex biomechanical events necessitate careful examination to ensure secondary injuries are not overlooked during the initial assessment.
4. Ligamentous Sprains
An ankle sprain is defined as the stretching or tearing of one or more ligaments within the joint. Lateral ankle sprains account for the vast majority of these injuries. The anterior talofibular ligament is the weakest component of the lateral complex and is almost invariably the first structure to fail during an inversion event.
If the inversion force continues, the calcaneofibular ligament may subsequently tear. Isolated injuries to the posterior talofibular ligament are rare and typically occur only in the context of a complete joint dislocation. The clinical signs of a sprain include rapid localized swelling, ecchymosis, and pain upon palpation over the affected ligament.
Medial ankle sprains involving the deltoid ligament are notably less frequent. They are often associated with concurrent fractures of the fibula and require a thorough radiographic evaluation to exclude subtle osseous injuries.
5. Grading Ankle Sprains
Clinicians utilize a standardized grading system to classify the severity of ligamentous injuries. This classification directs the treatment plan and provides a prognostic timeline for recovery.
| Sprain Grade | Structural Damage | Clinical Presentation |
|---|---|---|
| Grade I | Microscopic stretching of ligament fibers without macroscopic tearing. | Mild tenderness, minimal swelling, no joint instability, normal weight-bearing. |
| Grade II | Partial tearing of the ligament complex. | Moderate pain and swelling, localized ecchymosis, mild to moderate joint instability. |
| Grade III | Complete rupture of the affected ligaments. | Severe swelling and ecchymosis, significant pain, inability to bear weight, profound joint instability. |
Properly grading the injury is crucial. While a Grade I sprain may resolve within days, a Grade III rupture often requires functional bracing and extended physical therapy to restore proprioception and mechanical stability.
6. High Ankle Sprains
A high ankle sprain, clinically known as a syndesmotic sprain, involves damage to the ligaments connecting the distal tibia and fibula. These injuries are typically caused by external rotation forces applied to a dorsiflexed foot, frequently seen in contact sports.
Unlike lateral sprains, syndesmotic injuries do not exhibit pronounced, localized swelling on the outer ankle. Instead, patients report pain radiating up the lower leg, especially during weight-bearing activities or when the foot is actively rotated outward.
Recovery from a high ankle sprain is notably prolonged compared to standard lateral sprains. The syndesmosis experiences significant mechanical stress with every step, delaying the healing process. Severe syndesmotic disruption may lead to a widening of the ankle mortise, necessitating surgical stabilization with screws or flexible tension devices.
7. Ankle Fractures
Fractures of the ankle joint can involve the medial malleolus, the lateral malleolus, the posterior malleolus, or a combination of these structures. The severity of the fracture dictates whether conservative casting or surgical fixation is required.
Bimalleolar fractures involve both the medial and lateral malleoli, fundamentally destabilizing the joint. Trimalleolar fractures additionally involve the posterior aspect of the tibia. These complex injuries almost uniformly require open reduction and internal fixation to restore the anatomical alignment of the mortise.
The Danis-Weber classification system categorizes lateral malleolar fractures based on the location of the fracture line relative to the syndesmosis. Fractures occurring above the syndesmosis typically indicate a disruption of this critical fibrous joint and require meticulous surgical evaluation.
8. Tendon Injuries
The tendons crossing the ankle joint, particularly the Achilles tendon and the peroneal tendons, are susceptible to traumatic injury. The peroneal tendons course behind the lateral malleolus and are responsible for everting the foot. A forceful inversion injury can strain these tendons or cause them to subluxate out of their protective groove.
Achilles tendon ruptures frequently occur during sudden acceleration or jumping movements. Patients often report hearing a distinct pop and feeling a sensation resembling a strike to the back of the heel. Clinical examination reveals a palpable gap in the tendon and a profound weakness in plantarflexion.
Tendon injuries require specific diagnostic approaches. While osseous fractures are visible on standard radiographs, evaluating tendon integrity often necessitates advanced soft tissue imaging techniques to determine the extent of tearing or degeneration.
9. Clinical Evaluation and Diagnosis
The evaluation of an ankle injury begins with a detailed patient history, focusing on the specific mechanism of trauma and the ability to bear weight immediately following the event. The physical examination involves inspecting for swelling, bruising, and visible anatomical deformity.
Palpation is performed systematically to identify areas of maximal tenderness. The clinician assesses the medial and lateral malleoli, the base of the fifth metatarsal, and the navicular bone. Specific ligamentous tests, such as the anterior drawer test, are utilized to evaluate mechanical joint laxity indicative of complete ligament ruptures.
Neurovascular assessment is a mandatory component of the examination. The clinician must verify the presence of distal pulses, specifically the dorsalis pedis and posterior tibial arteries, and assess intact sensation to ensure that a displaced fracture or severe swelling has not compromised the limb blood supply.
10. The Ottawa Ankle Rules
To reduce unnecessary radiation exposure and optimize healthcare resources, clinicians widely apply the Ottawa Ankle Rules. This validated clinical decision tool determines the necessity of obtaining radiographic imaging following acute ankle trauma.
According to these rules, ankle radiographs are only required if there is pain in the malleolar zone accompanied by bone tenderness at the posterior edge or tip of the lateral malleolus, bone tenderness at the posterior edge or tip of the medial malleolus, or an absolute inability to bear weight both immediately after the injury and in the emergency department.
Foot radiographs are indicated if there is pain in the midfoot zone accompanied by bone tenderness at the base of the fifth metatarsal, bone tenderness at the navicular bone, or an inability to bear weight. Strict adherence to these rules safely filters out minor soft tissue injuries that do not require x-ray evaluation.
11. Diagnostic Imaging
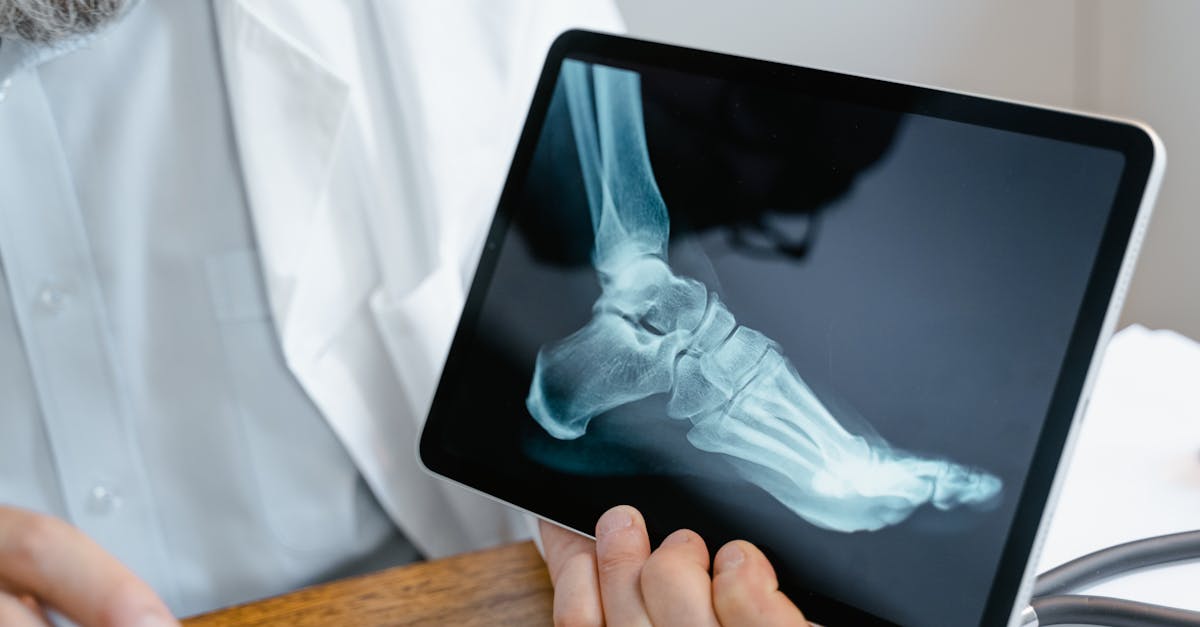
When clinical evaluation indicates potential osseous involvement, standard radiographic imaging is the first-line diagnostic modality. A complete ankle series includes anteroposterior, lateral, and mortise views. The mortise view is specifically angled to assess the clear space between the talus and the malleoli, providing critical information regarding joint congruity.
If a complex fracture is identified on plain films, a Computed Tomography scan may be ordered. This imaging technique provides detailed three-dimensional reconstructions of the bony architecture, assisting orthopedic surgeons in preoperative planning for intricate joint reconstructions.
Magnetic Resonance Imaging is rarely indicated in the acute setting of a standard ankle sprain. However, it is the optimal modality for evaluating chronic ankle pain, persistent instability, occult osteochondral lesions of the talus, or suspected tendon ruptures that fail to resolve with conservative management.
12. Acute Management and the RICE Protocol
The initial management of soft tissue ankle injuries focuses on controlling the localized inflammatory response. The traditional cornerstone of early treatment is the RICE protocol, an acronym standing for Rest, Ice, Compression, and Elevation.
Rest involves protecting the joint from further mechanical stress, often utilizing crutches or a rigid walking boot. Ice is applied intermittently to induce peripheral vasoconstriction, limiting the influx of inflammatory exudate and providing localized analgesia. Compression with an elastic bandage helps control swelling by increasing interstitial hydrostatic pressure. Elevation utilizes gravity to promote the lymphatic drainage of accumulated fluid back toward the central circulation.
Early, protected weight-bearing is now favored over prolonged immobilization for simple sprains. Encouraging controlled movement enhances blood flow, prevents muscle atrophy, and promotes the optimal alignment of healing collagen fibers.
13. Rehabilitation and Physical Therapy
Comprehensive rehabilitation is essential for preventing chronic ankle instability and recurrent injuries. Following the acute inflammatory phase, physical therapy focuses on restoring full range of motion, increasing muscular strength, and retraining proprioception.
Proprioception is the unconscious perception of joint position in space. Ligamentous injuries disrupt the microscopic nerve endings that provide this feedback. specialized balance exercises, utilizing tools such as wobble boards, are mandatory to retrain the neuromuscular pathways and protect the joint during dynamic activities.
Strengthening exercises target the peroneal muscles on the lateral aspect of the lower leg. These muscles serve as dynamic stabilizers of the ankle and can help compensate for any permanent ligamentous laxity resulting from a severe sprain.
14. Surgical Interventions
Surgical intervention is indicated for unstable fractures, complete syndesmotic disruptions, and selected full-thickness tendon ruptures. Open reduction and internal fixation involve utilizing surgical plates and screws to perfectly realign the fractured bone fragments, ensuring the mortise is entirely congruent.
For chronic ligamentous instability that fails extensive physical therapy, surgical reconstruction may be necessary. Procedures such as the Broström-Gould repair involve anatomically tightening and reattaching the stretched lateral ligaments to the fibula, restoring mechanical stability to the joint.
Postoperative care requires a period of strict non-weight-bearing immobilization, followed by a graduated rehabilitation program. Surgical success relies heavily on patient compliance with postoperative protocols and dedicated participation in physical therapy.
15. Frequently Asked Questions (FAQ)
1. How can I tell if my ankle is sprained or broken?
While severe sprains and fractures can both cause significant swelling and pain, the inability to bear weight on the foot and exquisite tenderness directly over the bony bumps of the ankle are strong indicators of a potential fracture requiring an x-ray.
2. Should I apply heat or cold to a fresh ankle injury?
You should always apply a cold compress or ice pack during the first forty-eight hours. Cold reduces blood flow, which limits swelling and provides pain relief. Applying heat early will increase inflammation and significantly worsen the swelling.
3. Is it better to keep my injured ankle completely still or try to walk on it?
For a standard sprain, brief initial rest is good, but early, protected walking using a brace or crutches is actually better for healing than keeping it completely immobilized. Movement promotes blood flow and helps realign healing tissues.
4. Why does my ankle still feel weak months after a severe sprain?
Severe sprains can stretch ligaments permanently and damage the microscopic nerves that control balance. Without specific physical therapy focused on balance and strengthening, the ankle will remain mechanically loose and prone to re-injury.
5. Do all ankle fractures require surgery?
No. If the fractured bone is perfectly aligned and the joint remains stable, it can often be treated successfully with a cast or a specialized walking boot. Surgery is only required when the bones are displaced or the joint structure is fundamentally unstable.
16. Bibliography
Disclaimer: The content is for informational purposes only and does not replace medical advice. Always consult your doctor for personalized treatment.




