
1. Introduction
A toe nail bed laceration is a traumatic disruption of the specialized soft tissues situated beneath the hard nail plate of the foot. The toes, particularly the hallux (the great toe), are frequently subjected to severe mechanical trauma. Whether from a dropped heavy object, a stubbing injury against a hard surface, or sporting accidents, the resulting crush forces frequently damage the delicate nail matrix and the underlying bone.
The medical management of a toe nail bed laceration requires specific considerations distinct from injuries on the hand. The foot bears the entire weight of the human body and is enclosed in a dark, warm, and often moist footwear environment. This makes toe injuries particularly susceptible to virulent bacterial and fungal infections. Furthermore, a painful, improperly healed toe nail can significantly alter a patient’s gait, leading to secondary mechanical issues in the knee, hip, or lower back.
Through rigorous clinical evaluation, meticulous decontamination, and precise surgical repair under local anesthesia, physicians can effectively manage these injuries. The primary clinical objectives are to prevent bone and soft tissue infections, accurately approximate the nail matrix to ensure normal nail regrowth, and implement proper footwear modifications to allow the patient to return to pain-free ambulation.
2. Anatomy of the Toe and Nail Unit
To effectively diagnose and repair a toe nail bed laceration, one must understand the complex anatomy of the perionychium, the anatomical term for the entire nail unit. The visible, rigid component is the nail plate, composed of densely layered, translucent keratin.
The nail plate rests upon the nail bed, a highly vascular, specialized soft tissue structure securely adhered to the periosteum (outer layer) of the underlying distal phalanx bone. The nail bed consists of two functional zones. The proximal region, located deep beneath the skin fold at the base of the nail, is the germinal matrix, responsible for the generation of new nail cells.
The distal region, extending to the tip of the toe, is the sterile matrix. Its primary function is to provide a smooth, flat adherence surface for the growing nail plate. If the sterile matrix is scarred or uneven due to an unrepaired laceration, the regrowing nail will detach, split, or become severely deformed, a condition particularly problematic when wearing restrictive shoes.
3. Mechanisms of Traumatic Foot Injury
The physical forces responsible for the trauma dictate the clinical characteristics of the laceration. Crush injuries are overwhelmingly the most common mechanism for toe nail bed lacerations. When a heavy object, such as a piece of furniture or a dropped weight, strikes the toe, the soft tissue of the nail bed is violently compressed between the rigid nail plate above and the distal phalanx bone below.
This crushing force typically results in a stellate (star-shaped) or bursting laceration of the delicate nail bed. The tissue edges are often ragged, severely contused, and surrounded by significant bleeding. Crush injuries to the toe also carry a remarkably high risk of fracturing the underlying bone.
Sharp trauma, though less common, can occur if a person steps barefoot on a sharp object like broken glass or sheet metal. These injuries create clean, linear incisions but can penetrate deeply, potentially severing the underlying flexor or extensor tendons that control the movement of the toe.
4. Subungual Hematoma and Mechanical Stress
A hallmark clinical finding following significant toe trauma is a subungual hematoma, a localized collection of blood trapped in the tight, unyielding space between the nail bed and the hard nail plate.
Because the space is confined, the bleeding rapidly generates intense hydrostatic pressure, leading to excruciating, throbbing pain that worsens when the foot is in a dependent (hanging down) position. The presence of a large subungual hematoma strongly suggests a laceration of the underlying nail bed.
If the nail plate remains firmly attached and aligned, the physician may perform trephination, creating a small hole in the nail to drain the blood and relieve the pressure. However, if the nail is loose, partially avulsed, or if an underlying fracture is suspected, the nail plate is typically removed to directly visualize and repair the lacerated tissue.
5. Identifying Underlying Phalangeal Fractures
The anatomical proximity of the nail bed to the distal phalanx bone means that any significant crush injury to the toe carries a high risk of an underlying bone fracture. A severe trauma that lacerates the nail bed frequently results in a tuft fracture (a shattering of the tip of the bone).
When a nail bed laceration occurs concurrently with a distal phalanx fracture, it is clinically classified as an open, or compound, fracture. This elevates the clinical severity significantly, as the broken bone is exposed to the external environment through the lacerated soft tissue, creating a high-risk scenario for osteomyelitis (a severe bone infection).
Consequently, standard plain radiographs (X-rays) in multiple views are an absolute necessity in the initial clinical evaluation for any significant toe crush injury or suspected nail bed laceration.
6. The Role of the Sterile and Germinal Matrices
The anatomical realignment of the sterile and germinal matrices is the primary surgical objective. The sterile matrix provides the smooth track necessary for the nail plate to adhere. If a laceration here heals with a raised, bumpy scar, the regrowing nail will be forced upward, creating a thickened, painful deformity that will rub constantly against the inside of a shoe.
Furthermore, if the germinal matrix at the base of the nail is severely damaged or scarred, it may permanently lose its ability to produce keratin, resulting in a permanently absent or severely stunted nail.
Meticulous surgical repair utilizing fine suturing techniques ensures that these delicate matrices heal as a continuous, flat surface, providing an unimpeded pathway for future, healthy nail growth.
7. Contamination and Infection Risks in the Foot
The feet present a unique and significant infection risk compared to the hands. Toes are in constant proximity to the ground and are frequently exposed to dirt, environmental bacteria, and fungal organisms. The enclosed, warm, and often sweaty environment inside footwear creates an ideal breeding ground for microbial proliferation.
A laceration that breaches the nail unit introduces these pathogens into a closed, complex tissue space. Puncture wounds through the nail, particularly those occurring through the rubber soles of shoes (like sneakers), carry a specific risk of Pseudomonas aeruginosa infection, an aggressive bacterium that thrives in moist environments.
In injuries involving an underlying open fracture, the risk of deep bone infection is substantial. Thorough, high-pressure irrigation and aggressive mechanical decontamination of the wound bed are absolute prerequisites before any surgical closure is attempted.
8. Clinical Assessment and Radiological Imaging
The clinical evaluation begins with a detailed history of the injury mechanism and assessing the patient’s footwear at the time of the accident. The physician evaluates the neurovascular integrity of the toe, checking capillary refill to ensure adequate blood flow and testing sensation to rule out digital nerve damage.
The physical appearance of the nail unit is scrutinized. A nail plate that is partially torn off, severely crushed, or displaced from the eponychium (the cuticle) indicates a severe underlying nail bed laceration requiring surgical exploration.
Radiological imaging is crucial. Multi-view X-rays of the affected foot are obtained to definitively diagnose or rule out a distal phalanx fracture. The presence of a fracture dictates the necessity for prophylactic oral antibiotics and influences the specific method of postoperative immobilization.
9. Data Summary: Toe Nail Bed Injury Profiles
Understanding the severity and type of injury guides the clinician in selecting the appropriate treatment strategy.
| Injury Classification | Clinical Findings | Standard Management Strategy |
|---|---|---|
| Simple Subungual Hematoma | Intact nail plate, painful dark blood collection | Trephination (draining blood), nail remains intact |
| Simple Laceration | Linear tear, nail plate partially lifted | Nail removal, precise suturing of sterile matrix |
| Crush Laceration with Fracture | Stellate tear, tuft fracture on foot X-ray | Debridement, suturing, antibiotics, rigid splinting |
| Avulsion Injury | Missing portion of nail bed tissue | Complex repair, potential tissue grafting required |
10. Achieving Digital Nerve Block Anesthesia
The toe is exceptionally dense with sensory nerve endings, rendering the exploration and repair of a nail bed laceration intolerably painful without profound anesthesia. The standard technique is a digital nerve block.
The physician injects a local anesthetic, such as lidocaine or bupivacaine, into the web spaces at the base of the injured toe, targeting the digital nerves before they branch outward. This technique completely numbs the entire digit from the base to the tip.
Using a digital block provides a painless surgical field without injecting fluid directly into the traumatized toe tip. Injecting into the tip itself would cause immense pain due to the tight tissue compartments and would physically distort the delicate anatomy of the nail bed, complicating the precise alignment required for repair.
11. Nail Plate Removal and Wound Decontamination
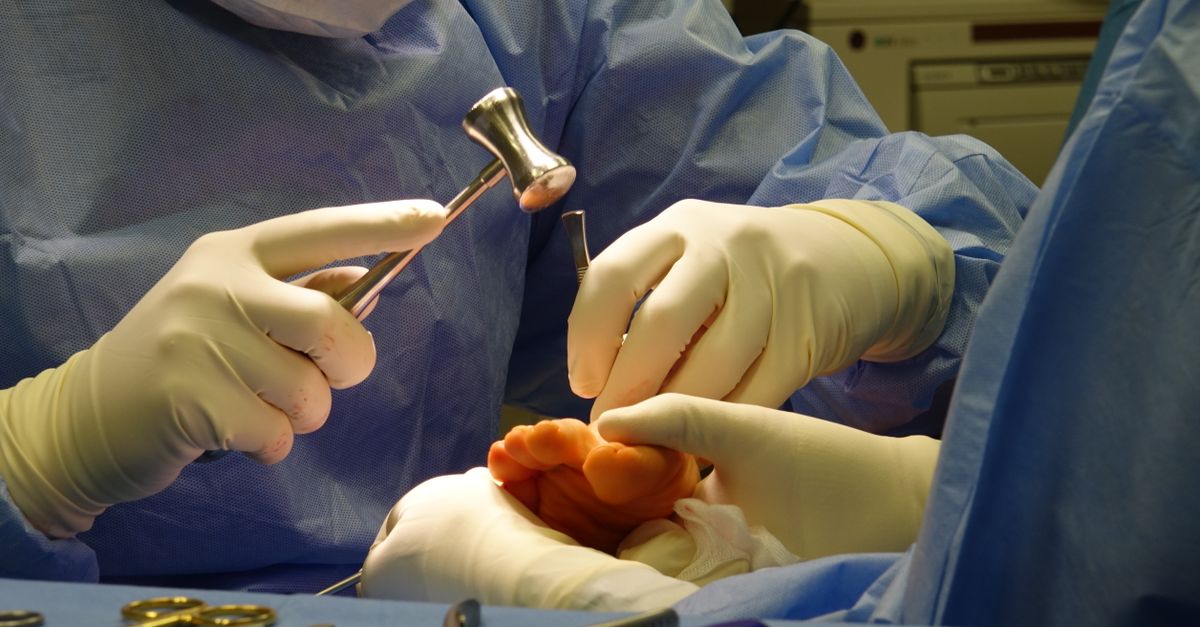
Once the toe is completely anesthetized, the physician exposes the lacerated nail bed. If the nail plate is partially avulsed or severely damaged, it is carefully elevated and removed from the surrounding skin folds using a specialized surgical instrument.
The removed nail plate is not discarded; it is soaked in a sterile antiseptic solution, as it may be utilized later in the procedure as a biological splint.
With the nail bed exposed, the wound undergoes rigorous decontamination. The physician flushes the area with copious amounts of sterile normal saline to remove clotted blood and environmental debris. The clinician meticulously debrides the wound, trimming away any crushed, non-viable tissue tags to create clean margins that can be precisely approximated.
12. Surgical Repair of the Nail Bed
The surgical repair of the toe nail bed is a microsurgical procedure. The tissue is exceptionally fragile. The physician utilizes fine, absorbable sutures, typically composed of rapidly dissolving materials like chromic gut.
These specific sutures are chosen because they dissolve naturally, eliminating the need for a painful suture removal procedure weeks later on a highly sensitive, healing toe. The sutures are placed meticulously to align the edges of the sterile matrix perfectly, creating a smooth, flat surface.
If the laceration extends proximally into the germinal matrix or the surrounding skin folds (the paronychia), these structures must also be carefully realigned and sutured to prevent the formation of scar tissue that could block or permanently disfigure the base of the growing nail.
13. Splinting with the Native Nail Plate
Following the meticulous suturing of the nail bed, the tissue must be protected and maintained in a flat position while it heals. The gold standard technique is to use the patient’s own native nail plate as a biological splint.
The physician places the cleaned nail plate back onto the repaired nail bed, gently tucking the proximal edge back under the skin fold at the base of the toe. This prevents the skin fold from scarring shut, which would block the new nail from growing outward. The nail plate is secured in place with a single suture or medical adhesive.
If the native nail plate was destroyed or lost at the scene of the accident, the physician may substitute it with a piece of sterile medical foil or customized silicone tubing to act as a synthetic splint, serving the exact same protective and anatomical purpose.
14. Postoperative Care and Footwear Modifications
Proper postoperative management is essential for an uncomplicated recovery. The toe is dressed with a non-adherent sterile pad, gauze, and a protective bandage. Evaluating the patient’s tetanus immunization status is mandatory, given the high likelihood of environmental contamination in foot injuries.
If the laceration involved an underlying tuft fracture (an open fracture), the patient is prescribed a short course of prophylactic oral antibiotics to prevent the development of osteomyelitis.
Footwear modifications are absolutely critical. The patient must wear a specialized, rigid-soled surgical shoe or an open-toed postoperative sandal for several weeks. This protects the fragile repair from accidental bumps and eliminates the mechanical pressure that a standard, closed-toe shoe would place on the healing tissue.
15. Long-Term Nail Growth and Ambulation
The physiological healing of a toe nail bed laceration requires significant time and patience. The splinted native nail plate will eventually detach and fall off after a few weeks as the tissue beneath it heals.
Toe nails grow significantly slower than fingernails. The new nail plate generated by the germinal matrix grows at a rate of approximately one millimeter per month. It typically takes nine to eighteen months for a complete, new nail to grow from the base to the tip of the great toe.
Even with flawless surgical repair, the new nail may exhibit temporary ridges, grooves, or minor thickening during the first growth cycle. The patient should be reassured that the final cosmetic and functional outcome cannot be accurately judged until the nail has completely regrown and remodeled over the course of a full year.
16. When to Seek Urgent Medical Care
While minor toe scrapes can be managed at home, specific signs indicate a severe nail bed injury requiring professional evaluation. If a toe sustains a crush injury resulting in a large, rapidly expanding, intensely painful collection of blood under the nail, medical care is required to relieve the pressure and evaluate for a laceration.
Immediate medical attention is mandatory if the nail plate is torn completely off, partially detached, or pushed out of its normal anatomical position.
Furthermore, if an older foot wound develops increasing redness, expanding swelling, intense throbbing pain, or begins to drain foul-smelling pus, these are critical signs of a developing infection in the enclosed spaces of the digit that necessitates urgent medical and pharmacological management.
17. Frequently Asked Questions (FAQ)
1. Will my toe nail grow back normally after being crushed?
If the nail bed was precisely repaired and the germinal matrix was not permanently destroyed by the trauma, the nail usually grows back normally. However, it can take up to 18 months, and temporary ridges or minor deformities are common during the first growth cycle.
2. Why did the doctor put my detached toe nail back on?
The hard nail plate acts as the perfect, custom-fit splint. It protects the delicate stitches, keeps the nail bed flat while it heals, and prevents the skin fold at the base of the nail from scarring shut, which would block new nail growth.
3. Does getting a needle in the toe hurt a lot?
The initial injection for the digital nerve block at the base of the toe causes a brief, sharp pinch and a burning sensation. However, once the anesthetic takes effect, the entire toe becomes completely numb, and you will feel no pain during the repair.
4. When can I wear normal shoes again?
You will likely need to wear an open-toed or rigid-soled surgical shoe for a few weeks to protect the repair. Once the tissue is sufficiently healed, your physician will clear you to return to wide, comfortable, closed-toe shoes.
5. What should I do if the splinted nail falls off early?
The native nail plate will eventually detach as the tissue heals beneath it. If it falls off after a few weeks, it is usually fine. If it falls off within the first few days, contact your physician, as the nail bed may need additional protection.
18. Bibliography
Disclaimer: The content is for informational purposes only and does not replace medical advice. Always consult your doctor for personalized treatment.

